How to Lower Triglycerides Naturally: What Works for Metabolic Health
High triglycerides often improve when the underlying metabolic pattern is addressed.
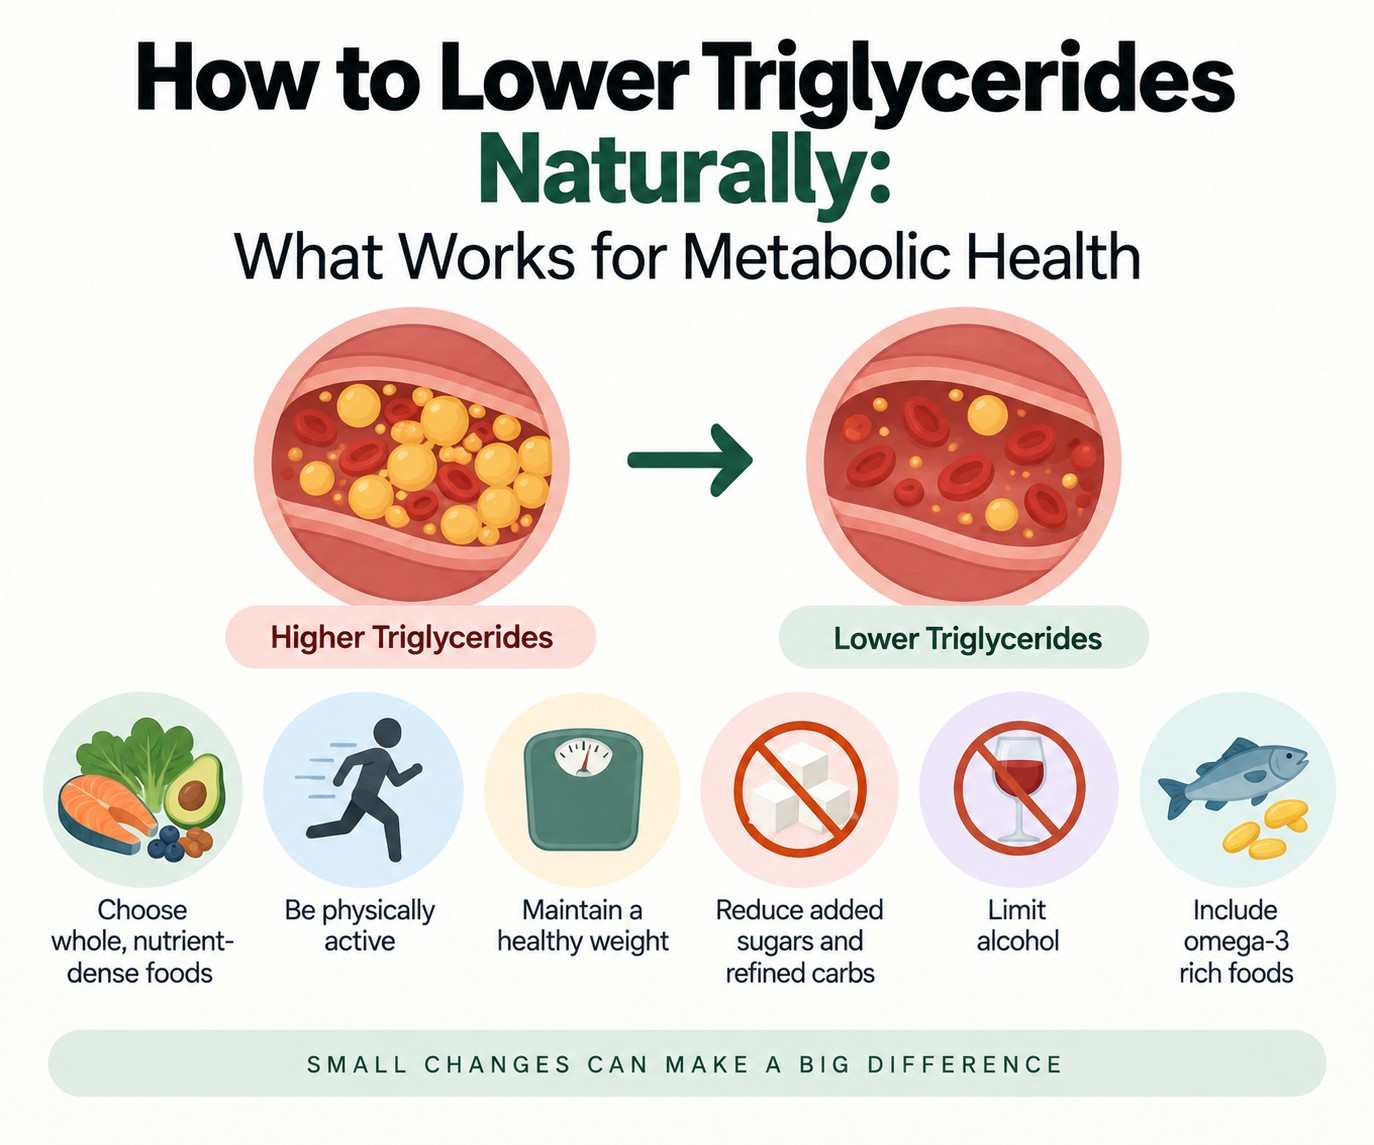
High triglycerides are common, often silent, and easy to misunderstand. They are not simply a number caused by eating fat. Triglycerides are a type of fat that circulates in the blood and stores unused energy. Levels can rise when the body is regularly handling more energy, refined carbohydrate, alcohol, or metabolic stress than it can use efficiently. They may also be affected by diabetes, insulin resistance, fatty liver, hypothyroidism, kidney disease, some medicines, and inherited lipid conditions.
A single elevated result should not cause panic, but it should lead to a thoughtful review. The right response depends on how high the value is, whether the test was fasting, your LDL cholesterol and ApoB, blood pressure, HbA1c, waist circumference, family history, medicines, and alcohol intake. Very high triglycerides can increase the risk of pancreatitis and need prompt medical attention. Do not attempt to manage a markedly abnormal report with internet advice alone.
What triglycerides tell us about metabolic health
Triglycerides are carried in blood particles after meals and during fasting. When insulin resistance is present, the liver may produce more triglyceride-rich particles and the body may clear them less effectively. This pattern can occur alongside lower HDL cholesterol, rising fasting insulin, abdominal weight gain, fatty liver, and increasing glucose values. That is why triglycerides are useful as part of a wider metabolic assessment rather than as an isolated dietary score.
For a clearer look at early insulin resistance, read Fasting Insulin: The Most Useful Test Almost Nobody Orders. HbA1c is another important marker, although it does not capture every stage of metabolic risk. Our article on what prediabetes really means explains why trends and clinical context matter.
Start with the factors that have the greatest effect
For many people, reducing sugary drinks, desserts, frequent refined snacks, and large portions of highly processed carbohydrates makes a meaningful difference. This does not mean every carbohydrate is harmful. Pulses, vegetables, fruit, and minimally processed grains provide fibre and nutrients. The more useful question is whether meals are built around protein, fibre, and satisfying whole foods or around rapidly digested, low-fibre products that are easy to overeat.
Alcohol deserves a direct discussion. Even amounts that seem modest can increase triglycerides in some people, especially when levels are already high or fatty liver is present. If your clinician recommends avoiding alcohol for a period, treat that as part of the test of what is driving the result. Do not assume a drink is harmless because it is not sweet.
Exercise helps because muscle changes fuel handling
Regular movement improves the way muscle uses fuel. Brisk walking, cycling, swimming, and other aerobic activities are valuable, while resistance training helps preserve or build muscle mass. A practical starting point may be a short walk after meals and two to three weekly strength sessions adjusted to your fitness and medical history. Consistency is more valuable than an intense plan that disappears after two weeks.
Muscle health is also central to healthy ageing. See Why Muscle Is a Longevity Organ for the connection between strength, glucose control, mobility, and long-term function. If weight loss is appropriate, protecting muscle through resistance exercise and adequate protein is especially important.
Sleep, stress, and fatty liver are not side issues
Short or fragmented sleep can make appetite regulation and glucose control harder. Persistent stress may affect eating patterns, activity, and recovery. Snoring with daytime sleepiness can indicate sleep apnea, which deserves assessment rather than simply more caffeine. These factors do not replace nutrition and activity, but they often determine whether a plan is sustainable.
Fatty liver commonly overlaps with raised triglycerides and insulin resistance. Normal liver enzymes do not always rule it out, and an elevated enzyme does not identify the cause by itself. A clinician may consider history, examination, laboratory tests, and imaging where appropriate. A structured approach through iMedi Longevity can connect metabolic biomarkers, lifestyle, and preventive follow-up rather than treating one result in isolation.
When medicines are part of the plan
Lifestyle changes are foundational, but they are not the whole answer for everyone. Diabetes medicines, lipid-lowering treatment, and triglyceride-specific therapies may be appropriate depending on your levels and overall cardiovascular or pancreatitis risk. Do not stop a prescribed statin or other medicine because one number improves. Likewise, do not start supplements marketed for triglycerides without checking dose, interactions, quality, and whether they actually fit your clinical situation.
ApoB can add useful information when triglycerides are raised because it reflects the number of cholesterol-containing particles that can contribute to artery disease. Read ApoB vs LDL Cholesterol to understand why a standard lipid report may not always show the complete risk picture.
Make a repeatable plan
Choose two or three changes you can maintain for several weeks: replace sweet drinks with water, build protein and vegetables into two meals a day, walk after dinner, reduce alcohol, or begin supervised strength work. Then repeat the lipid profile at the interval recommended by your clinician. The aim is not perfection. It is a trend toward better metabolic health, lower risk, and more physical capacity.
If you have very high triglycerides, severe upper abdominal pain, nausea, vomiting, or fever, seek urgent medical care. For a preventive review of triglycerides, glucose, blood pressure, body composition, and cardiovascular risk, contact iMedi to arrange a consultation.
How to interpret a triglyceride result properly
A triglyceride result is most useful when you know the conditions under which it was measured. A non-fasting sample can be appropriate for routine lipid screening, but a clinician may request a fasting repeat when the result is unexpectedly high, when pancreatitis risk needs assessment, or when the laboratory cannot calculate other lipid values reliably. Recent alcohol intake, a very large meal, acute illness, uncontrolled glucose, and some medicines can influence the reading.
Look at the actual units and the laboratory reference range rather than comparing numbers from different reports without checking. A small change between two tests may represent normal biological or laboratory variation. A persistent pattern is more meaningful. The clinician will also ask whether triglycerides are mildly, moderately, or severely raised because the urgency and treatment priorities are different. Cardiovascular prevention is important across the range, while very high levels bring a more immediate concern about pancreatitis.
Why triglycerides and HDL often move together
A pattern of high triglycerides and lower HDL cholesterol is frequently seen with insulin resistance. This does not mean that raising HDL directly is the treatment goal. Instead, the pattern can be a clue to look more closely at abdominal adiposity, glucose regulation, activity, diet, sleep, and liver health. Improving the underlying metabolic environment may lower triglycerides and change the wider lipid profile.
LDL cholesterol can appear acceptable even when the number of atherogenic particles remains elevated. Non-HDL cholesterol and ApoB may therefore add context for selected patients. Treatment decisions should reflect total cardiovascular risk, including age, blood pressure, smoking, diabetes, kidney health, family history, and previous cardiovascular disease. No online calculator or single biomarker replaces a clinical discussion.
Secondary causes that should not be missed
High triglycerides are sometimes a sign of another issue that needs direct treatment. Poorly controlled diabetes can cause a substantial rise. Hypothyroidism, chronic kidney disease, pregnancy, and some liver conditions may contribute. Medicines that can affect triglycerides include selected steroids, retinoids, oestrogens, antipsychotic medicines, immune therapies, and some blood-pressure or HIV treatments. This does not mean a prescribed medicine should be stopped. It means the medication list should be reviewed with the prescriber.
Family history also matters. Very high triglycerides, repeated pancreatitis, or early cardiovascular disease in close relatives can suggest an inherited tendency. Genetic susceptibility often interacts with lifestyle and metabolic factors, so a person can have both. A physician may recommend testing relatives or referral for specialist assessment when the pattern is unusual or severe.
What an Indian eating pattern can look like
Improving triglycerides does not require abandoning familiar Indian food. The practical change is often in proportions, preparation, and frequency. Build meals around vegetables, dal, chana, rajma, soy, eggs, fish, chicken, paneer, curd, or other suitable protein sources. Choose less-refined grains in portions that fit your activity and glucose response. Limit repeated servings of sweets, bakery products, fried snacks, sweetened tea or coffee, packaged juice, and sugar-sweetened beverages.
Fruit does not need to be removed automatically. Whole fruit provides fibre and is different from juice, which is easier to consume quickly and in larger quantities. Nuts and seeds can fit a balanced diet, but they are energy dense, so portions still matter when weight reduction is part of the plan. People with kidney disease, diabetes medicines, digestive conditions, or other dietary restrictions need individual guidance.
An eight-week plan that produces useful information
Start by recording the habits most likely to influence your result. For the first two weeks, note sugary drinks, alcohol, meal timing, steps, strength sessions, and sleep duration without trying to perfect everything. Then choose a small set of changes. Replace liquid sugar, reduce or avoid alcohol, add a post-meal walk, include a protein source at each main meal, and schedule two resistance-training sessions each week if medically suitable.
During weeks three to eight, focus on repetition. A missed workout or celebration meal does not invalidate the plan. Return to the next useful action. If you monitor weight or waist circumference, use consistent conditions and look at the trend. When the agreed period is complete, repeat only the tests recommended by your clinician. Review what changed, what did not, and whether medication or further investigation is needed.
Common mistakes when trying to lower triglycerides
One mistake is focusing only on dietary fat while continuing frequent refined carbohydrate or alcohol. Another is starting an extreme diet that produces rapid weight loss but cannot be maintained. Some people buy multiple supplements before checking for diabetes, thyroid disease, fatty liver, or medication effects. Others celebrate a lower triglyceride result while ignoring blood pressure, ApoB, smoking, or worsening glucose.
The better approach is integrated. Use triglycerides as one signal within a plan that protects the heart, liver, pancreas, muscle, and long-term function. Improvements that last are usually built from ordinary behaviours performed consistently, combined with appropriate medical treatment where indicated.
Frequently Asked Questions (FAQs)
1. Can high triglycerides be lowered naturally?
Often they can improve with changes to food quality, alcohol intake, activity, sleep, and weight management where appropriate. Some people also need medication.
2. Are triglycerides high because I eat too much fat?
Not necessarily. Refined carbohydrate, alcohol, insulin resistance, diabetes, fatty liver, medicines, and genetics can all contribute.
3. Should I fast before a triglyceride test?
Follow the laboratory and clinician instructions. Fasting may be requested in selected situations, especially when triglycerides are high.
4. What triglyceride level is dangerous?
Risk depends on the number and the whole clinical picture. Very high values can raise pancreatitis risk and should be reviewed promptly.
5. Can exercise lower triglycerides without weight loss?
Yes. Regular activity can improve metabolic health even when scale weight changes little.
6. Does fish oil always lower triglycerides?
Prescription and supplement products differ. Ask a clinician before using omega-3 products, particularly if you take blood thinners or have other conditions.
7. How often should triglycerides be rechecked?
Your clinician can recommend an interval based on the result, treatment plan, and other risk factors.
This article is for educational purposes and does not replace personalised medical advice. Please consult a qualified physician before making changes to your treatment, medication, or health screening plan.
